MS diagnosis relies on multiple findings and can remain uncertain as symptoms and evidence evolve. A revised diagnosis doesn’t necessarily mean a mistake was made.
When an MS diagnosis changes
Christina Applegate’s revised diagnosis raises a question that gets lost in the word “misdiagnosis”: does a diagnosis changing mean someone made a mistake? Not necessarily. Applegate, an American actor and longtimeWhy doctors work with probabilities
A medical diagnosis isn’t always a definitive answer backed by one decisive test. Some diagnoses describe diseases with identifiable causes; others name patterns of symptoms and examination findings that help clinicians communicate, study outcomes, and choose care. Between those poles are conditions supported by varying kinds and strengths of evidence: symptoms, exam findings, blood tests, imaging, biopsies, electrical studies, treatment response, and the course of illness over time. Some findings are “pathognomonic”—so specific that their presence establishes a particular disease. Most aren’t. A test result may be associated with a condition only part of the time, or may appear in several different disorders. Clinicians therefore combine evidence and estimate how likely a diagnosis is, rather than waiting for certainty that medicine often can’t provide. MS is especially difficult to pin down. It’s a chronic autoimmune disease affecting the central nervous system. Diagnosis generally requires evidence of inflammatory lesions occurring at different times and in different locations, such as the brain, spinal cord, or optic nerves, while also ruling out other conditions that could explain the findings. Outside certain MS subtypes, there’s no single test that confirms the disease. Here’s the thing: diagnostic certainty also has to be weighed against the risks of getting more information. A brain biopsy might clarify a case, but the procedure’s danger can outweigh what the result would change. Clinicians have to ask what a diagnosis is for: will it alter treatment, prognosis, follow-up, or management, or is it serving mainly as a working label?A working diagnosis can guide treatment
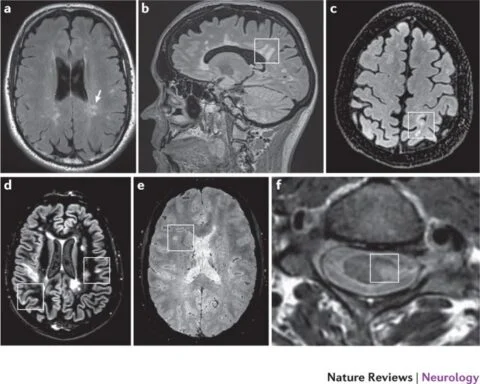
Effective disease-modifying treatments for MS have been available since the 1990s, and treatment options have improved. As treatments become available, clinicians may need to decide not only whether a patient meets a disease definition, but whether the evidence supports treating them. That can shape diagnostic criteria and clinical practice. Based on the public information the author has seen, Applegate appeared to meet criteria for MS treatment after a proper evaluation. In such cases, MS may become the working diagnosis even though some patients later prove not to have the disease. Medicine sometimes treats before certainty when delaying care could be more harmful than treating someone who doesn’t ultimately have the condition. Applegate’s lack of response to treatment prompted her doctors to reconsider. They repeated the evaluation, used a newer MRI technique, and, taking the new information together with her course of illness, concluded she likely never had MS. The available account doesn’t explain exactly how much weight each piece of evidence carried. Still, a reassessment in response to new information is part of sound clinical reasoning; a diagnosis isn’t supposed to be permanent when the evidence points elsewhere.Care without a final label
Applegate reportedly heard the revised assessment as “good news,” but felt it left her without an answer. That reaction is understandable. Patients are often led to expect that a precise diagnosis is the key to treatment, an expectation reinforced by medical dramas such as *Dr. House*. In practice, a specific label isn’t always necessary to provide useful care—and a wrong label isn’t better than none. Neurologists can rule out conditions that are active, worsening, or require targeted treatment, then address symptoms and function directly. They may find something treatable, such as low B12, without knowing whether it explains the patient’s complaints. They can treat that finding, manage symptoms, and keep watching how the illness develops. For some patients, ruling out dangerous or progressive diseases is itself a meaningful result. The remaining explanation may be a subtle or non-progressive condition that can be managed symptomatically, or a problem that has passed and left effects to address. Neither possibility requires a precise diagnosis, and both may be preferable to an active destructive disease. The hard part is communicating this uncertainty. Clinicians can underestimate how strongly patients may expect a name for what’s happening, and how unsettling it is to leave an appointment without one. Applegate has spoken publicly about a serious neurological experience in the hope of helping others. The author wishes her well and argues that a changed diagnosis needn’t end her advocacy. For people navigating MS, the uncertainty itself may be an important part of the story.About the author
Steven Novella, MD, is an academic clinical neurologist at Yale University School of Medicine and the founder and executive editor of Science-Based Medicine. He hosts and produces the weekly podcast The Skeptics’ Guide to the Universe and writes NeuroLogicaBlog, which covers neuroscience, science, skepticism, critical thinking, and their intersections with media and society. He has also created two courses for The Great Courses and wrote a book on critical thinking, also titled The Skeptics’ Guide to the Universe. View all of his posts.
This article appears in the Neuroscience/Mental Health category.



Discussion
Sign in to join the discussion.